
NEWS 2 Chart: Complete Guide for Nurses and OSCE Preparation

The NEWS 2 chart is the standard observation chart used across the NHS to record a patient’s vital signs and turn them into a single early warning score. NEWS2 stands for National Early Warning Score 2, and the chart was developed by the Royal College of Physicians (RCP) to help staff spot acute illness and deterioration early and respond in a consistent way. If you are a nurse, an international nurse joining the NHS, or a candidate preparing for the NMC OSCE, you will need to read this chart accurately. This guide explains what is recorded, how the score is built, what Scale 2 is, how monitoring and escalation relate to the score, and where the official chart lives. It also explains how NEWS2 appears in NMC OSCE materials. Educational use only. This guide is written by Medax OSCE Academy for learning. It does not replace the official RCP chart, your employer’s policy or clinical judgement. Medax is not affiliated with, endorsed by or approved by the NHS, NHS England, the NMC or the Royal College of Physicians. What Is a NEWS2 Chart? A NEWS2 chart is a colour-coded observation chart. Staff record routine physiological measurements on it, score each one, and add the scores together. The total helps the team judge how unwell the patient may be and how urgently to respond. The RCP describes NEWS as a simple aggregate scoring system built on measurements that are already routinely taken. NHS England and NHS Improvement endorsed it as the recommended early warning system for adults in the NHS in England. The RCP report also notes it should support, not replace, clinical judgement. In short: the chart tracks trends over time, flags deterioration early and gives everyone a common language. What Does NEWS2 Stand For? NEWS2 stands for National Early Warning Score 2. The “2” marks the updated version published in 2017, which refined the original NEWS launched in 2012. The main changes were: a separate oxygen saturation scoring scale (Scale 2) for patients with confirmed hypercapnic respiratory failure; “new confusion” added to the consciousness assessment, changing AVPU to ACVPU; reordering of parameters to follow the ABCDE approach; a clearer emphasis on the link between a score of 5 or more and possible sepsis; a redesigned colour scheme that works better for people with red–green colour blindness. What Is Recorded on a NEWS2 Chart? Six physiological parameters are scored, plus a weighting for supplemental oxygen. The chart also records the oxygen delivery device and flow rate. Parameter What is recorded Notes Respiration rate Breaths per minute Scored high or low Oxygen saturation (SpO₂) Percentage, using Scale 1 or Scale 2 Scale choice is a clinical decision (see below) Air or oxygen Whether the patient is on supplemental oxygen Adds 2 points if on oxygen Systolic blood pressure mmHg Only systolic is scored Pulse rate Beats per minute Scored high or low Consciousness ACVPU: Alert, new Confusion, Voice, Pain, Unresponsive Anything other than Alert scores 3 Temperature °C Both high and low temperatures score The RCP says the core scoring section of the chart should stay consistent nationally, while the rest of the chart may be adapted locally (for example, to record pain or urine output). How Does NEWS2 Scoring Work? Each parameter scores between 0 and 3. The further a reading is from the normal range, the higher the score. The six parameter scores are added, and 2 points are added if the patient needs supplemental oxygen to maintain their prescribed saturation. The total is the aggregate NEWS2 score. The table below summarises the RCP Scale 1 scoring. Always check readings against the official RCP chart; this table is a learning summary. Parameter 3 2 1 0 1 2 3 Respiration rate ≤8 9–11 12–20 21–24 ≥25 SpO₂ Scale 1 (%) ≤91 92–93 94–95 ≥96 Air or oxygen Air Oxygen Systolic BP (mmHg) ≤90 91–100 101–110 111–219 ≥220 Pulse (bpm) ≤40 41–50 51–90 91–110 111–130 ≥131 Consciousness Alert C, V, P or U Temperature (°C) ≤35.0 35.1–36.0 36.1–38.0 38.1–39.0 ≥39.1 Two points people often miss: A single red score. A score of 3 in any one parameter is treated as a trigger for urgent review, even if the total is low. New confusion scores 3. If it is unclear whether confusion is new, the RCP says to treat it as new until confirmed otherwise. Some patients have naturally low blood pressure or a low resting pulse, for example, and the RCP notes that other information can explain unusual values. That is why the score is an aid to assessment, not a verdict. What Is NEWS2 Scale 2? Scale 2 is a separate oxygen saturation scoring scale on the NEWS2 chart. It is for patients who have confirmed hypercapnic respiratory failure (often type 2 respiratory failure, most commonly related to COPD) and whose prescribed target saturation is 88–92%. Why it exists: patients with hypercapnic respiratory failure can be harmed if given too much oxygen. Under Scale 1, a target of 88–92% would score as abnormal and could push staff to give more oxygen than is safe. Scale 2 adjusts scoring so that 88–92% scores 0. The RCP’s rules for using it: Use it only for patients confirmed to have hypercapnic respiratory failure on blood gas analysis, in a previous or current admission. A competent clinical decision maker must choose it, and the decision must be recorded in the clinical notes. In all other cases, use Scale 1. The scale you are not using should be clearly crossed out on the chart. Practical point: Scale 2 is not something to switch to because a patient has COPD or a low reading. If you are unsure which scale applies, ask a senior clinician and follow local policy. NEWS2 Monitoring Frequency The RCP recommends that the NEWS2 score informs how often observations are done, and that the frequency is recorded on the chart. The RCP’s recommended minimums are: NEWS2 result RCP recommended minimum frequency Aggregate score 0 12-hourly Aggregate score 1–4 4–6 hourly
Upcoming Physical OSCE Training Dates Medax Academy

Medax is running onsite, hands-on OSCE training sessions for Adult Nursing, Paediatric Nursing, Nursing Associate, and Mental Health candidates over the coming months. Each session is delivered in person, giving candidates the chance to practise under exam conditions with direct trainer feedback something online prep alone can’t fully replicate. Training Schedule Month Dates Format October 12–16 Oct Onsite, physical training November 16–20 Nov Onsite, physical training December 14–18 Dec Onsite, physical training Each week-long session runs across all four pathways, so candidates can choose the intake that fits their exam date and travel plans. Who Should Attend Candidates preparing for their OSCE in Adult Nursing Candidates preparing for their OSCE in Paediatric Nursing Candidates on the Nursing Associate pathway Candidates preparing for their OSCE in Mental Health nursing Why Onsite Training Physical sessions give candidates structured station practice, real-time examiner-style feedback, and peer practice with other candidates on the same pathway the kind of exam-condition rehearsal that’s hard to replicate remotely. Spaces for each intake are limited to keep group sizes practical for hands-on feedback, so early booking is recommended, particularly for the October dates. 👉 Register your place now
Tracheostomy Care Training for Care Staff: Full Guide
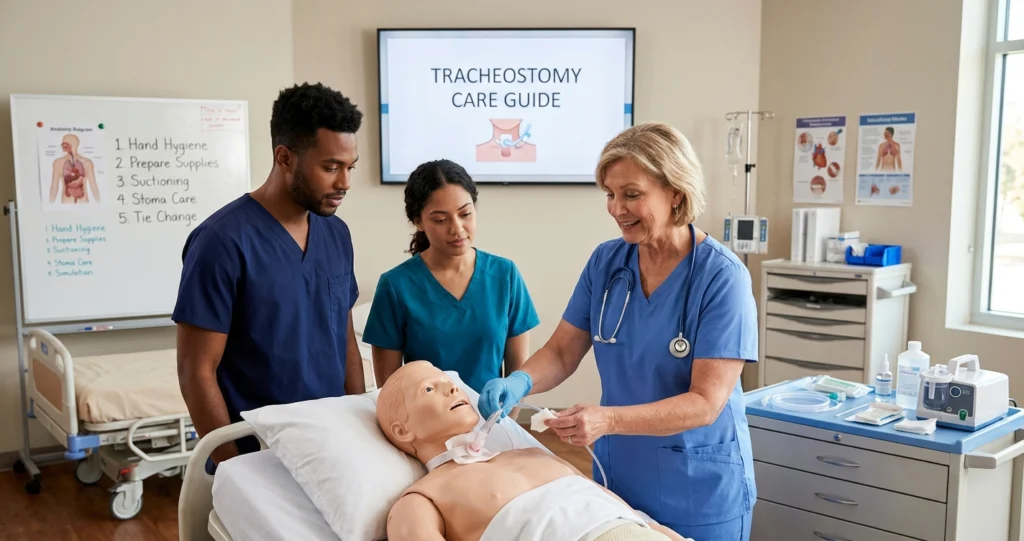
A tracheostomy is one of the highest-risk pieces of equipment a care worker will ever be responsible for. Get it wrong a blocked tube, a missed sign of infection, a fumbled emergency response and the consequences can be immediate and severe. Tracheostomy care training for care staff exists precisely because this isn’t a skill that can be safely learned from a leaflet or a single classroom session. This guide sets out what genuine tracheostomy care training should cover, who needs it, how competency should actually be assessed, and the mistakes that most commonly put both service users and providers at risk. What Does Tracheostomy Care Actually Involve? A tracheostomy is a surgically created opening in the neck into the windpipe (trachea), usually with a tube in place to keep the airway open. People living with a tracheostomy in a community or supported living setting typically need support with: Stoma site care cleaning around the opening and checking for signs of infection or skin breakdown Tube changes (where the care worker is trained and signed off to assist or perform this) Suctioning to clear secretions and keep the airway clear Humidification and management of secretions, particularly important since a tracheostomy bypasses the nose’s natural warming and moistening function Cuff management, where a cuffed tube is in place Recognising and responding to emergencies a blocked tube, accidental decannulation (the tube coming out), or bleeding Some individuals also require ventilator support alongside their tracheostomy, which adds a further layer of clinical complexity and typically demands training beyond general tracheostomy care alone. Why This Isn’t a Skill to Learn “On the Job” Informally A blocked or displaced tracheostomy tube can compromise someone’s airway within minutes. This is not an area where care staff should be learning through trial and error, gradually picking things up from colleagues, or relying on a single training session completed months or years earlier without refreshment. CQC’s fundamental standards require staff to have the skills, knowledge, and experience necessary for the care they deliver. For tracheostomy care specifically, inspectors expect to see individualised, hands-on competency assessment not just a certificate confirming someone attended a session. A worker who can describe the suctioning procedure in an interview but has never been observed performing it safely under supervision has not been adequately trained, regardless of what their file says. Core Components of Tracheostomy Care Training 1. Understanding the Anatomy and Purpose Staff need a working understanding of why the person has a tracheostomy, what type of tube they have, and what “normal” looks like for that specific individual because tube types, cuff status, and care routines vary significantly between people. 2. Suctioning Technique Safe suctioning depth, duration, technique, and recognising when suctioning is and isn’t appropriate delivered through supervised, hands-on <a href=”https://medax-group.com/clinical-skills-training/”>clinical skills training</a> using appropriate equipment and simulation before any real-world practice. 3. Stoma Site Care and Infection Prevention Cleaning technique, dressing changes where relevant, and recognising early signs of infection, skin breakdown, or granulation tissue that need escalation to a clinician. 4. Humidification and Secretion Management Understanding why humidification matters, how to use the equipment involved (heat and moisture exchangers, nebulisers where prescribed), and recognising when secretions indicate a problem rather than normal variation. 5. Emergency Response This is the single most critical component. Staff need rehearsed, not just described, responses to: A blocked tube (recognising the signs and knowing the clearance protocol) Accidental decannulation (the tube coming out) and safe re-insertion where the worker is trained and authorised to do this, or immediate escalation where they are not Bleeding from the stoma site Signs of respiratory distress 6. Tube Changes Not every care worker will be trained or authorised to change a tracheostomy tube this varies by provider policy, the individual’s care plan, and local clinical governance arrangements. Where care staff are involved, this requires the most intensive level of supervised practice and sign-off of any component. Who on Your Team Needs This Training? Role Typical Training Scope Support Worker / Healthcare Assistant Stoma care, suctioning, humidification, recognising and escalating emergencies Senior Support Worker All of the above, plus supervision of others and incident escalation Registered Nurse (clinical oversight) Full competency including tube changes where applicable, assessment of others, liaison with ENT/respiratory specialists Bank/Agency staff Same individualised competency standard as permanent staff before deployment A frequent and serious gap: bank or agency staff being deployed to support someone with a tracheostomy without their own competency being individually verified for that specific person’s equipment and care plan, on the assumption that agency-provided training is equivalent. It often isn’t, and this is exactly the kind of gap that surfaces during a serious incident review. Online vs Onsite Training: What Actually Works Factor Online / Virtual Onsite / In-Person Best for Anatomy, theory, infection control principles, documentation standards Suctioning technique, emergency drills, stoma care, tube change practice Assessment rigour Knowledge checks only Direct observation and physical competency sign-off Risk if used alone for practical skills High cannot verify physical technique or reaction speed under pressure Low assessor confirms safe, timely technique Suitability for emergency response training Poor on its own Essential emergency scenarios need to be physically rehearsed, not just read about Theory can be delivered flexibly online. Suctioning technique, emergency decannulation response, and tube changes cannot be safely verified without in-person, supervised practice. Any provider offering “complete” tracheostomy training through e-learning alone is not offering a genuinely safe standard for this particular skill area. A blended model flexible theory plus mandatory in-person assessment reflects how Medax structures its <a href=”https://medax-group.com/complex-care-training/”>complex care training</a>. Common Mistakes in Tracheostomy Care Training Treating attendance as competency. Sitting through a session on suctioning is not the same as being observed safely performing it under time pressure. No individualised sign-off per service user. A worker competent with one person’s tube type and routine isn’t automatically ready for a different individual with different equipment or a different baseline. Infrequent emergency drills. Blocked tube and decannulation emergencies are, thankfully, rare for any given individual which means the skill
How the NMC Actually Updates OSCE Stations (And Why Memorising Old Ones Won’t Save You)

Every few months, a wave of panic moves through international nursing exam groups: “New OSCE stations announced!” “Leaked marking criteria!” “This scenario is coming up next month!” If you’re preparing for your NMC OSCE, it’s easy to feel like you’re chasing a moving target. Here’s the reassuring truth: the way the NMC updates the Test of Competence OSCE is a well-established, deliberate process, not a random or chaotic one. Once you understand how and why it works, the anxiety around “new stations” mostly disappears, because you realise that solid preparation was never really about memorising a fixed list in the first place. The OSCE Structure Doesn’t Change The Content Within It Does This is the single most important thing to understand. The Objective Structured Clinical Examination for nurses consists of ten stations, structured the same way regardless of when you sit it: Station Type Purpose Typical Count APIE (Assessment, Planning, Implementation, Evaluation) Assesses your ability to manage a patient’s care journey through a linked scenario 4 linked stations Clinical Skills Tests practical hands-on competencies, often in linked pairs 4 stations Professional Values (PV) A silent, written station assessing professional accountability and communication 1 station Evidence-Based Practice (EBP) A silent, written station assessing critical appraisal of research and evidence 1 station Nursing associates sit a slightly different distribution (three AIE stations, five skills stations, and two PV/EBP stations), but the same principle applies: the format is fixed even as the specific clinical scenario within each station changes over time. The NMC has explicitly confirmed that its ongoing content refreshes will not change the number of stations candidates sit only the specific scenarios and skills tested within the existing structure. Why the NMC Refreshes Station Content at All According to the NMC’s own published guidance, the refresh process exists for three main reasons: Clinical relevance. Healthcare practice evolves new evidence, updated guidelines, and changing patient safety priorities mean that stations need to reflect what’s actually happening in UK clinical settings today, not what was current when the test was designed. Retiring overused stations. Any station that’s been in circulation for a long time becomes more likely to be shared, discussed, and effectively “leaked” between candidates, which undermines its ability to fairly assess competence. Retiring these stations protects the integrity of the exam for everyone. Introducing new applicable skills. As the scope of nursing practice shifts, new clinical skills and scenarios are introduced so the test continues to reflect what a newly registered nurse should genuinely be able to do. This is the same underlying process, cycle after cycle it isn’t a one-off event tied to a single announcement, but an ongoing feature of how the NMC maintains the exam. Why Trying to Memorise Specific Stations Is a Losing Strategy It’s tempting to think that if you could just get hold of the “current” station list, you’d walk in prepared. In practice, this approach fails for several reasons: Content rotates faster than leaked lists can keep up. By the time a specific scenario has circulated widely enough for you to hear about it, it may already be scheduled for retirement precisely because it’s become too widely known. Examiners assess your reasoning, not your script. Even within a familiar station type, examiners are marking your clinical reasoning, communication, and safety awareness not whether you recite a memorised answer. A candidate who has genuinely internalised the underlying standard will handle a slightly unfamiliar variation far better than a candidate who memorised one specific version and freezes when it’s slightly different. The NMC has publicly cautioned against this. Official NMC-linked preparation materials explicitly warn candidates not to attempt to memorise or rote-learn marking criteria, since these are subject to periodic change and this approach undermines genuine competence-based assessment. What to Actually Prepare Against Instead of chasing specific leaked scenarios, focus your preparation on the things that remain stable across every content refresh: 1. The NMC Code Every Professional Values station and much of your general conduct across all stations is assessed against the NMC’s Code, structured around four themes: prioritise people, practise effectively, preserve safety, and promote professionalism and trust. If you can consistently apply these four themes to any scenario, you’re prepared for whatever specific PV station you’re given. 2. The Standards of Proficiency for Your Field Whether you’re training for Adult, Mental Health, Paediatric, or Midwifery registration, the underlying standards of proficiency define what a newly registered professional in your field must be able to do. Stations are designed to test these standards not to test trivia. 3. The Station Format Itself Knowing exactly how an APIE sequence flows, how much time you have per skills pairing, what a silent written EBP station requires, and how documentation is assessed gives you a structural advantage that holds regardless of the specific clinical content. 4. Time Management Within Each Station Type A huge number of candidates lose marks not because they lack clinical knowledge, but because they run out of time completing required documentation or miss steps under pressure. This is a skill you can practise and improve independent of which exact scenario you’re given. A Realistic Way to Track Genuine Updates Rather than relying on screenshots and forwarded messages, here’s a more reliable approach: Source Reliability Official nmc.org.uk OSCE and Test of Competence pages Highest this is the primary source Your NMC-approved test centre’s own bulletins (Northampton, Ulster, Leeds) High often reflects confirmed operational detail Established OSCE preparation providers who explicitly cite and verify against NMC sources Moderate to high, depending on how transparently they source claims Social media forwards and unverified blog posts Low treat as “worth checking,” not “confirmed” If a piece of information about a station change can’t be traced back to the NMC itself or your test centre, treat it as a rumour worth verifying, not a fact worth building your entire preparation around. How This Should Shape Your Study Plan A preparation plan built around stable fundamentals rather than chasing rumours typically looks like this: Weeks 1–2: Deep review
NMC OSCE Resit After a Test Centre Closure: What Happens to Your Booking

Finding out that your OSCE test centre has closed while you’re mid-way through resits is stressful, especially if you’re already juggling work, family, and the emotional weight of the exam itself. If you originally sat your OSCE at Oxford Brookes University or Northumbria University and haven’t completed your resits yet, this guide walks through exactly what happens next. We’ll keep this practical: what the NMC’s process actually involves, what you need to send, and what to expect at your new centre. First, the Reassuring Part Your progress isn’t lost. If you passed some stations and failed others, you still only need to resit the stations you didn’t pass a centre closure doesn’t reset your attempt count or force you to redo stations you’ve already passed. What changes is where you take that resit, not what you need to complete. Which Centres Have Closed Oxford Brookes University OSCE delivery ended 31 July 2026. Northumbria University OSCE delivery ended 19 February 2026 (affecting both RN/RM and nursing associate routes). If you sat your first attempt at either of these centres and still have stations to resit, this guide applies to you. Step-by-Step: How to Transfer Your Resit Step 1: Confirm You Need to Transfer If your original OSCE attempt was at Oxford Brookes or Northumbria and you have not yet completed all your resits, you’ll need to move to one of the currently approved centres: University of Northampton Ulster University Leeds Teaching Hospitals NHS Trust Step 2: Choose Your New Centre You get to choose which of the three remaining centres you’d prefer for your resit. Consider travel distance, availability, and how soon you want to sit your resit, since demand at the remaining centres has increased following the closures. Step 3: Email the New Centre Directly This is the step candidates most often get wrong the transfer isn’t automatic. You need to email your chosen new centre yourself, and your email needs to clearly identify itself as a transfer request. Including a subject line that references the transfer (for example, referencing “Northumbria Transfer Request” or the equivalent for Oxford Brookes) helps the centre process your request quickly and avoid delays. In your email, it helps to include: Your full name as registered with the NMC Your NMC PIN or application reference number Your original test centre and the date of your last attempt Which stations you still need to resit, if known Your preferred resit dates or availability Step 4: Wait for Confirmation Once the new centre reviews your request and confirms they can accommodate you, they will: Confirm your booking directly with you Notify the NMC that your centre has changed From this point forward, all future resits must take place at this new centre you won’t be able to move between centres again unless there’s a further centre closure. This is standard NMC policy for resits generally, not something unique to the transfer process. Step 5: Complete Your ID Check (If Needed) If you hadn’t completed your identity verification check at your original centre, this needs to happen at your new centre before you can sit your resit. ID checks are typically appointment-only, and appointment availability can vary by centre, so it’s worth arranging this as early as possible once your transfer is confirmed don’t leave it until close to your resit date. If your ID check was already completed at your original centre, you generally won’t need to repeat it, but always confirm this directly with your new centre to be certain. Step 6: Prepare for Your Resit This is the part fully within your control. A centre transfer doesn’t change the exam content, marking criteria, or station structure it only changes location. So your preparation strategy should focus on the stations you didn’t pass previously, using your original feedback as a guide. What Your Resit Feedback Tells You When you don’t pass an OSCE attempt, the NMC provides feedback identifying which specific stations and elements you were unsuccessful in. This feedback is genuinely valuable it tells you exactly where to focus your preparation time rather than re-revising everything from scratch. If you’re not sure how to interpret this feedback or turn it into a focused study plan, working through it with an experienced OSCE trainer can save significant time compared to generic revision. A Realistic Timeline for Your Resit Task Suggested Timing Confirm which centre you’re transferring to As soon as you know your original centre has closed Send your transfer request email Immediately after choosing your new centre Complete any outstanding ID check As soon as your transfer is confirmed Begin focused resit preparation on failed stations Straight away don’t wait for your booking confirmation Book your resit date As early as availability allows (remember the 10-day minimum gap between sittings) Sit your resit On your confirmed date Remember that NMC rules require a minimum of 10 days between OSCE sittings, and you’re permitted a maximum of three attempts as part of a single application. If you don’t pass by your third attempt, your application closes and you’d need to start a new application after a required waiting period so it’s worth taking this preparation seriously rather than treating a resit casually. Common Questions Candidates Have During This Process “Do I lose my passed stations if I transfer centres?” No. You only need to resit the stations you didn’t pass, regardless of which centre you transfer to. “Will the marking be different at my new centre?” No. Every NMC-approved centre applies the same national marking criteria and blueprint. A different location does not mean different standards. “What if my preferred new centre can’t accommodate me?” You can approach another approved centre instead. The choice of which centre to transfer to is yours, subject to their availability. “Can I go back to my original centre later?” No once your transfer is confirmed, your new centre becomes your centre for any further resits, in line with standard NMC resit policy. Turning a Stressful Transfer Into a Focused
NMC OSCE Test Centres 2026: Where to Book Now That Two Centres Have Closed

If you searched for “NMC OSCE test centres 2026” because you’re not sure where to book, you’re not alone. Two of the five centres that used to run the OSCE have closed in the last twelve months, and a lot of the information floating around in nursing WhatsApp groups and Facebook pages is out of date. This guide sets out exactly which centres are currently approved by the Nursing and Midwifery Council (NMC) to deliver the Objective Structured Clinical Examination (OSCE), what changed, and what it practically means for your booking, your resit, and your preparation timeline. We’ll keep the tone simple and factual. No panic, no guesswork just what’s confirmed and what you need to do next. Quick Answer: The Current NMC-Approved OSCE Centres As of now, there are three NMC-approved centres delivering the OSCE for internationally educated nurses, midwives, and nursing associates: Test Centre Status University of Northampton Open and accepting bookings Ulster University Open and accepting bookings Leeds Teaching Hospitals NHS Trust Open and accepting bookings Oxford Brookes University Closed since 31 July 2026 Northumbria University Closed since 19 February 2026 If you were planning to sit your OSCE at Oxford Brookes or Northumbria, you’ll need to book at one of the three remaining centres, or, if you already sat and failed a station there, follow the specific transfer process for resits (covered in detail in our related guide on resitting after a test centre closure). Why Do NMC OSCE Test Centres Close? It’s worth understanding this, because it isn’t unusual, and it isn’t a sign of anything wrong with the OSCE itself. The NMC works with a small number of university and NHS partners who are contracted to deliver the practical exam on its behalf. Contracts end, capacity changes, and partners sometimes step back from delivering the test this has happened more than once since the current Test of Competence structure was introduced. What matters for you as a candidate is simple: the exam itself, its structure, its marking criteria, and its standards haven’t changed because a centre closed. Only the list of places you can sit it has changed. What This Means If You Haven’t Booked Yet If you’re still at the stage of preparing for your CBT or getting ready to book your first OSCE attempt, the practical impact is straightforward: you now choose between three centres instead of five. Each delivers the same NMC-blueprinted test, with the same station structure and the same marking standards, regardless of location. Realistically, your decision will come down to: Location and travel cost how far you need to travel and whether you’ll need accommodation. Booking availability with fewer centres, popular exam dates can fill up faster, so it’s worth booking earlier than you might have previously. Familiarity with the environment some candidates prefer to visit or research a centre’s layout in advance through their preparation provider. None of the three current centres is “easier” than another. The OSCE is standardised precisely so that this isn’t the case the same clinical scenarios, timing, and marking criteria apply everywhere. What This Means If You Were Booked at Oxford Brookes or Northumbria If your booking was cancelled or you’re mid-way through resits at one of the closed centres, you are not starting from scratch. The NMC has confirmed a transfer process: You choose which of the remaining approved centres you’d like to resit at. You email that centre directly, including a specific reference in your subject line so they know it’s a transfer request. Once the new centre confirms it can accommodate you, they notify the NMC and your booking is updated. From that point, any further resits must be taken at your new centre you can’t switch back and forth. If your identity check hadn’t been completed at the closed centre, that also needs to happen at your new centre, and it’s worth knowing that ID check appointment availability can vary between centres. We’ve written a full step-by-step breakdown of this exact process, including what to put in your email and what to expect afterwards. Comparing the Three Approved OSCE Centres Here’s a general overview to help you plan. Always confirm current availability, fees, and location details directly with the centre before booking, as capacity changes throughout the year. Centre Region Best For University of Northampton East Midlands, England Candidates based in the Midlands or South England Ulster University Northern Ireland Candidates based in Northern Ireland or looking for shorter travel from Ireland Leeds Teaching Hospitals NHS Trust Yorkshire, England Candidates based in the North of England Wherever you sit your OSCE, the test itself is identical in structure: ten stations, covering assessment and care planning (APIE), clinical skills, professional values, and evidence-based practice. If you want a refresher on exactly how those stations work and how they’re marked, our detailed OSCE preparation resources cover this in full. Booking Timeline: What to Expect With fewer centres delivering the exam nationally, it’s sensible to build in extra lead time. A realistic planning timeline looks like this: Stage Suggested Timing Confirm your field-specific eligibility and pass your CBT Before booking OSCE Choose your preferred approved centre As early as possible Book your OSCE slot As soon as you’re ready don’t wait until the last minute given reduced centre capacity Begin structured OSCE preparation At least 6–8 weeks before your test date, ideally longer Attend your OSCE On your booked date Receive results Within 5 working days Common Mistakes Candidates Make Right Now Because this is a recent change, we’re seeing a few avoidable mistakes: Relying on outdated blog posts or social media groups that still list five centres, including the two that have closed. Assuming a resit automatically transfers without candidates actually emailing the new centre themselves it doesn’t happen automatically. Leaving booking too late, not accounting for the fact that three centres are now absorbing demand that used to be spread across five. Choosing a centre based on rumour about which one is “easier,” when in reality the exam
Can a US Nurse Work in the UK? What Your NCLEX Actually Gets You

Your NCLEX-RN, your state license, maybe a decade of bedside experience in a US hospital none of it transfers automatically to the UK. That’s the part most US nurses researching this don’t expect. It’s not that the UK doesn’t want US-trained nurses; it’s that the Nursing and Midwifery Council (NMC) doesn’t recognise any overseas nursing qualification, American or otherwise, without its own verification process first. Quick answer: Yes, a US-trained nurse can work in the UK, but you’ll need to register with the NMC through its international route first. Because the US sits outside the European Economic Area, this almost always means passing the NMC’s Test of Competence, a computer-based test (CBT) and a practical clinical exam (OSCE) regardless of your NCLEX-RN status or years of experience. Most US-trained nurses are exempt from the separate English language test (IELTS/OET), since the US is on the NMC’s list of majority English-speaking countries. Here’s what the actual process looks like, stage by stage, and where US nurses specifically tend to misjudge the timeline. Does a US Nursing License Transfer to the UK? No, not directly. The UK doesn’t have a reciprocal or mutual recognition agreement with US state nursing boards. Whether you trained through a BSN, ADN, or diploma programme, and however long you’ve held your RN license, the NMC treats your qualification the same way it treats any nursing qualification earned outside the UK and the EEA: it needs independent verification and assessment before you can register. This surprises a lot of US nurses, partly because reciprocity genuinely does exist between US states (a compact-license nurse can often work across state lines without extra exams), so it’s a reasonable assumption that something similar might apply internationally. It doesn’t. The NMC’s job is to confirm your training and clinical competence meet UK standards specifically, not simply to confirm you’re a licensed nurse somewhere else. The NMC Test of Competence: What US Nurses Actually Need to Pass Nurses trained outside the EEA which includes the US go through the NMC’s Test of Competence (ToC) as part of registration. It has two parts: CBT (Computer-Based Test): A multiple-choice exam covering nursing theory, numeracy, and UK clinical standards. It’s sat at a Pearson VUE test centre, and most candidates take it from their home country before travelling to the UK. OSCE (Objective Structured Clinical Examination): A practical, in-person exam at a UK test centre, assessing clinical skills, communication, and professional judgement against UK pre-registration standards, typically across a series of timed stations. You can sit these in either order, but both must be passed within two years of each other. There’s no exemption for years of US clinical experience, and NCLEX-RN success doesn’t substitute for either component the NMC is testing against UK nursing standards specifically, not US ones, which is exactly why the two exams exist. For a full walkthrough of the wider registration sequence around these tests, see our step-by-step guide to the NMC registration process. English Language Requirements for US Nurses This is where US nurses usually catch a break. The NMC accepts IELTS Academic or OET as evidence of English proficiency but it also exempts applicants trained in a recognised majority English-speaking country, and the United States appears on that list. In practice, this generally means US-trained nurses don’t need to sit IELTS or OET as part of NMC registration. That said, exemption criteria have specific conditions attached (relating to where your nursing education took place, not simply your nationality), so it’s worth confirming your own eligibility directly against the NMC’s current English language requirements guidance before assuming you’re exempt. If it turns out you do need to sit a test, our OET training programme is built around exactly this requirement. Step-by-Step: How US Nurses Register with the NMC Create an NMC online account and start your application as an internationally trained applicant. Submit qualification and identity documents nursing degree/diploma certificates, transcripts, proof of your active US license, and identity verification. Confirm your English language route: most US-trained applicants rely on the majority English-speaking country exemption rather than sitting IELTS/OET. Receive your Test of Competence invitation once your qualification is confirmed as meeting NMC requirements. Sit the CBT, generally from the US at a Pearson VUE centre. Travel to the UK to sit the OSCE at an approved test centre, once you’re authorised to do so. Complete health, character, and right-to-work checks, including a DBS (background) check. Receive your NMC PIN once both ToC components are passed and all checks are complete this is what makes you a registered nurse in the UK. Timelines vary by individual circumstances, document processing, and test centre availability, so treat any fixed number of months you see quoted online as a rough guide rather than a guarantee. Getting a Job Offer and a UK Work Visa NMC registration and a UK work visa are two separate processes that need to happen in tandem; passing your ToC doesn’t put you in the UK, and a visa alone doesn’t make you eligible to practise. Most US nurses come to the UK on the Health and Care Worker visa, a sub-route of the Skilled Worker visa designed for qualified nurses, doctors, and other regulated health professionals. At a high level, you’ll need: A confirmed job offer from a UK employer holding a Home Office sponsor licence A Certificate of Sponsorship from that employer, tied to your specific role A salary that meets the relevant threshold for registered nurses (this is reviewed periodically, so check the current figure rather than relying on an old quote) Proof of your English language ability nurses who’ve already met the NMC’s English requirement (including via the majority-English-speaking-country exemption) typically satisfy this for visa purposes too, but always confirm against current guidance since visa rules change independently of NMC rules UK immigration rules are updated regularly, so treat this section as a starting orientation rather than a final answer, and check gov.uk’s Health and Care Worker visa guidance directly before making any application
Can You Combine OET and IELTS Scores for NMC Registration? Here’s What Actually Happens

You sat OET, and your Listening, Reading and Speaking are exactly where the NMC wants them. Writing came in just under. So you book IELTS next, thinking you can add that one strong score to your OET results and submit both. It feels logical. It also isn’t how NMC score combining works. Quick answer: No, the NMC does not allow you to combine an OET result with an IELTS result. You can only combine scores across two sittings of the same test: two IELTS sittings, or two OET sittings. If your Listening, Reading, Writing and Speaking scores are split across OET and IELTS, only the scores from whichever test you sit twice can count toward your application. That single rule trips up more candidates than almost any other part of NMC’s English language requirements and it’s exactly what this guide unpacks: how genuine score combining works, what the required scores actually are, and what to do if your scores are currently split across two different tests. Can You Combine OET and IELTS Scores for NMC Registration? The short version: not with each other. The NMC’s own guidance is explicit that you can combine tests of the same type for example, two IELTS tests or two OET tests but you cannot combine an IELTS test with an OET test. It’s an understandable mix-up. Both tests assess the same four domains (listening, reading, writing, speaking), both are accepted by the NMC, and plenty of forum threads and outdated blog posts talk about “combining scores” without specifying which test they mean. But from the NMC’s perspective, OET and IELTS are two separate, non-interchangeable forms of evidence. If your first sitting was OET, your second sitting — the one you’re hoping to combine with it also needs to be OET. The same applies in reverse for IELTS. Understanding the NMC English Language Requirements Before you can register as a nurse or midwife with the NMC, you need to prove you can communicate safely and accurately in English with patients, colleagues, and in clinical documentation. This isn’t a formality; miscommunication in a clinical setting has real consequences, which is why the requirement is strict and specific. The NMC currently accepts exactly two tests as evidence: IELTS Academic (not IELTS General, IELTS Indicator, IELTS Online, or the One Skill Retake option none of these are accepted) OET (on Paper, on Computer, or OET@Home, all Nursing profession-stream) If you’re deciding between the two for the first time, our OET training programme page breaks down what each test actually involves. If you’ve already sat one test and are wondering about your next step, keep reading the combining rules below apply regardless of which test you started with. How Does Combining OET and IELTS Scores Work? Combining only works within one test type, and it isn’t as simple as “get one good score in each domain from anywhere.” To combine two sittings of IELTS, or two sittings of OET, you must: Sit both tests within 12 months of each other, and both must be dated no more than two years before the NMC assesses your complete application. Be tested in all four domains at each sitting. You cannot retake a single domain on its own — every sitting covers listening, reading, writing, and speaking together. Reach the full required score in each domain at least once across the two sittings — it doesn’t need to be the same sitting for every domain. Keep every other score, in both sittings, above a set minimum floor. This is the part people most often miss: even the domains you’re not relying on can’t fall too far below the pass mark, or the combination is rejected outright. That fourth condition is why a nurse can’t simply average a strong sitting against a weak one. A very low score in one domain, even if another domain compensates elsewhere, can invalidate the whole combination. Required IELTS and OET Scores for NMC Registration Domain IELTS Academic (single sitting) OET (single sitting) Listening 7.0 Grade B (350–440) Reading 7.0 Grade B (350–440) Writing 6.5 Grade C+ (300–340) Speaking 7.0 Grade B (350–440) Minimum floor when combining two sittings of the same test (every score, in both sittings, must sit at or above this line): Domain IELTS floor OET floor Listening 6.5 Grade C+ (300–340) Reading 6.5 Grade C+ (300–340) Speaking 6.5 Grade C+ (300–340) Writing 6.0 Grade C (250–290) Test scores are valid for two years from the date of the test, not the date the certificate was issued. Important Rules When Combining OET and IELTS Results No cross-test combining, ever. Two IELTS sittings or two OET sittings only. 12-month window between sittings. Sit them further apart than that and neither can be used in combination. All four domains, every sitting. Booking a single-skill retest (where the format allows it) doesn’t count toward combining. The floor applies to every score, not just the ones you’re relying on. A high Reading score doesn’t rescue a Listening score that falls beneath the minimum. Two years’ validity at the point of a complete application, not at the point you submit initial paperwork. If your NMC application review is delayed, older scores can expire mid-process. You need one qualifying score per domain across the two sittings but you cannot mix which domain came from where if that means using different test types. None of this is arbitrary; it’s designed to stop combining being used to paper over a genuine, consistent weakness in one skill area, while still giving a fair second chance for an off day. Example Scenarios Scenario 1: Passed OET in three sub-tests, missed Writing A nurse scores B in Listening, Reading, and Speaking on their first OET sitting, but only a C (below C+) in Writing. If they resit OET and score at least C+ in Writing the second time — with every other domain in both sittings still at or above C+ (or C for writing) — the combination is valid. Resitting IELTS instead would not help,
How to Get Preparation for an OET Course (2026 Nurse Guide)

For internationally educated nurses working toward UK registration, the Occupational English Test (OET) is often the first major hurdle. Unlike general English exams, OET is built entirely around healthcare communication listening to clinical consultations, reading medical texts, writing referral letters, and role-playing real patient conversations. That focus makes it more relevant to your day-to-day work, but it also means generic English study alone rarely gets you the score you need.If you’re asking how to get preparation for an OET course, this guide walks through exactly that: what OET actually tests, the score you need for NMC registration, a realistic step-by-step preparation path, how long it takes, and where structured training genuinely helps versus where self-study can work. This guide is written for internationally trained nurses, midwives and other healthcare professionals preparing for UK registration, as well as anyone comparing OET preparation options before committing time and money to a course. Quick answer: To prepare for an OET course, most nurses follow a structured programme covering all four modules Listening, Reading, Writing and Speaking with daily focused practice, full mock exams, profession-specific letter-writing practice, and speaking role-play rehearsal, typically over around six weeks of consistent study. Key Takeaways OET has four modules: Listening, Reading, Writing and Speaking, all built around healthcare scenarios. For NMC registration, nurses generally need a minimum of B in Listening, Reading and Speaking, and C+ in Writing. Most structured preparation programmes run for around six weeks of focused study. Writing and Speaking are the modules most candidates underestimate both need profession-specific practice, not just general English study. OET does not replace CBT or OSCE it is the English language evidence stage of NMC registration. What Is the OET, and Why Do Nurses Need It? The Occupational English Test (OET) is a healthcare-specific English language proficiency test, accepted by the Nursing and Midwifery Council (NMC) as evidence of English language ability for international nurses and midwives applying for UK registration. Unlike general English tests, every OET task is set in a healthcare context. You might listen to a doctor briefing a colleague, read an extract from a clinical guideline, write a discharge letter for a patient being transferred to a GP, or role-play explaining a procedure to an anxious patient. This is why nurses who prepare specifically for OET, rather than relying on general English study, tend to perform better the format, vocabulary and scoring criteria are all profession-specific. The Four OET Modules Explained OET Module Overview for Nurses Module What It Tests Typical Task Listening Understanding spoken healthcare English Consultation extracts, clinical handovers, presentations Reading Understanding written healthcare English Medical texts, guidelines, case notes Writing Producing a professional healthcare letter Referral, discharge or transfer letter based on case notes Speaking Professional spoken communication with patients Two profession-specific role plays with a trained interlocutor Listening and Reading are common across all professions taking OET. Writing and Speaking are profession-specific nurses are tested on nursing scenarios, which is why generic English courses often fall short: they don’t train you on the letter format, register or clinical vocabulary examiners are actually scoring. What Score Do You Need for OET? For NMC registration, the current accepted requirement is a minimum of Grade B in Listening, Reading and Speaking, and a minimum of Grade C+ in Writing. Results must generally be combined from no more than two sittings within a six-month period, subject to the NMC’s specific combining rules always check the current requirement on the NMC’s own site before booking, since English language requirements can be updated. OET Grades Required for NMC Registration Module Minimum Grade Needed Listening B Reading B Speaking B Writing C+ Step-by-Step: How to Prepare for an OET Course Step 1: Take a Diagnostic Practice Test Before choosing a course, sit a full practice test to see where you currently stand across all four modules. This tells you whether you need general English improvement, exam-technique coaching, or both. Step 2: Choose a Structured, Profession-Specific Course Because Writing and Speaking are nursing-specific, look for a course built around healthcare scenarios rather than generic English classes. A structured programme should include daily live teaching, not just pre-recorded content. Step 3: Build Medical Vocabulary and Grammar for Healthcare OET rewards precise, professional healthcare language. Regular vocabulary building, focused on clinical terms and register, makes a measurable difference to Writing and Speaking scores. Step 4: Practise Writing Referral, Discharge and Transfer Letters This is one of the most commonly underprepared areas. Practise converting case notes into a well-structured, correctly formatted healthcare letter, and get feedback on tone, structure and content selection not just grammar. Step 5: Rehearse Speaking Role Plays Speaking is tested through two role plays with a trained interlocutor. Practising out loud, ideally with feedback from a tutor or study partner, builds the fluency and confidence that reading alone cannot. Step 6: Sit Full-Length Mock Exams Under Timed Conditions Timing is a common reason candidates underperform. Full mock exams under exam conditions build stamina and help you manage pacing across all four modules. Step 7: Review Feedback and Target Weak Areas Use personalised feedback to focus your final weeks of preparation on your specific weaker module, rather than spreading study time evenly across all four. Step 8: Book Your Exam With Confidence Once your mock scores consistently meet the grades you need, book your OET sitting. Getting guidance on the booking process itself can help avoid administrative delays. How Long Does OET Preparation Take? This varies by starting English level, but most candidates benefit from a structured period of consistent, focused study rather than open-ended, unstructured revision. Structured course: Most comprehensive OET preparation programmes run for around six weeks of daily, focused study. Strong starting English: Candidates already close to the required grades may need a shorter, more targeted period focused on exam technique and letter-writing format. Building from a lower level: Candidates who need to strengthen general English first may need a longer runway before starting profession-specific OET preparation. Resit preparation: If retaking a
How to Get Into Paediatric Nursing in the UK

Paediatric nursing is one of the most rewarding careers in the NHS. If you’re wondering how to get into paediatric nursing, you’re joining thousands of aspiring and internationally trained nurses who want to care for children, support families, and make a genuine difference during some of the hardest moments of a child’s life. This guide walks through what a paediatric nurse actually does, the qualifications you’ll need, and the exact steps to take whether you’re a UK school leaver or an overseas nurse working towards NMC registration. What Does a Paediatric Nurse Do? A paediatric nurse cares for children from birth through to adolescence, across settings like hospital wards, neonatal units, community clinics, and paediatric intensive care (PICU). The role blends clinical skill with emotional intelligence, since you’re treating a patient while also supporting anxious parents and carers. Day to day, a children’s nurse might administer medication calculated for a child’s weight, monitor vital signs, support a family through a difficult diagnosis, or assist in emergency resuscitation. Family-centred care sits at the heart of the job — treatment plans are built around the whole family, not just the child. Paediatric nurses also play a critical safeguarding role, watching for signs of abuse or neglect and following strict protocols to protect vulnerable children. Essential Skills Succeeding as a paediatric nurse takes more than clinical knowledge. Employers and the NMC look for a specific mix of technical and interpersonal ability. Communication skills — explaining procedures to children in age-appropriate language and reassuring worried parents Clinical precision — accurate drug calculations and observations for patients whose vital signs vary hugely by age Emotional resilience — coping with distressing situations while staying calm and professional Safeguarding awareness — recognising and reporting signs of harm Teamwork — working closely with doctors, health visitors, and allied health professionals Adaptability — adjusting your approach for a newborn in neonatal care versus a teenager on a general ward Evidence-based practice — applying current clinical guidelines rather than outdated habits Step-by-Step Guide to Becoming a Paediatric Nurse 1. Meet the entry requirements. Most paediatric nursing degree UK programmes ask for five GCSEs (including English, maths, and science) plus A-levels or an equivalent Level 3 qualification. 2. Complete a nursing degree. You’ll need a BSc in Children’s Nursing, approved by the Nursing and Midwifery Council (NMC). These typically run three years full-time and combine university study with clinical placements in hospitals and community settings. 3. Undertake clinical placements. Placements are where theory becomes practice. You’ll rotate through wards, neonatal units, and community teams, building the hands-on competence needed to register. 4. Register with the NMC. Once you graduate, you apply for NMC registration, the legal requirement to practise as a nurse anywhere in the UK. 5. Apply for paediatric nursing jobs. With registration confirmed, you can apply directly to NHS trusts, children’s hospitals, and specialist units. 6. Continue your professional development. Many nurses go on to gain postgraduate qualifications in areas like PICU or neonatal care. Comparison Table: Routes Into Paediatric Nursing Route Who It’s For Typical Duration Key Requirement BSc Children’s Nursing (UK degree) UK school leavers, career changers 3 years A-levels or equivalent Nursing Apprenticeship UK healthcare assistants wanting to qualify while working 4 years Employer sponsorship, GCSEs Postgraduate Diploma (accelerated) Graduates with a related degree 2 years Relevant honours degree NMC Registration (International Route) Overseas-trained nurses Varies (CBT + OSCE) Overseas nursing qualification, IELTS/OET, CBT and OSCE pass Can International Nurses Become Paediatric Nurses? Yes. The UK actively recruits international nurses to fill NHS workforce gaps, and paediatric nursing is no exception. If you’re already a qualified nurse overseas, you don’t need to restart your degree. Instead, you go through the NMC’s international registration route. This involves an application review, an English language test (IELTS or OET), the Computer-Based Test (CBT), and the Objective Structured Clinical Examination (OSCE) the practical exam that confirms you can safely deliver care to UK standards. Understanding the Paediatric Nursing OSCE The paediatric nursing OSCE is a hands-on assessment where you demonstrate clinical and communication skills in simulated scenarios, such as medication administration, safeguarding conversations, and emergency response. Assessors mark you against strict NMC competency standards. It’s widely regarded as the most challenging part of the international nurse UK registration journey, mainly because candidates are assessed on UK-specific protocols, documentation, and paediatric-specific scenarios that may differ from their home country’s practice. This is exactly where structured preparation makes the difference between a pass and a resit. Medax Group’s Paediatric Nursing OSCE course is built specifically around the current NMC test plan, giving international nurses realistic practice stations, expert feedback, and confidence going into exam day. Tips for International Nurses Practise paediatric drug calculations daily errors here are a common reason for OSCE failure Rehearse safeguarding scenarios out loud, not just in your head Get familiar with UK documentation and NHS terminology before your exam Book structured mock OSCE sessions rather than relying on self-study alone Don’t underestimate the CBT treat it with the same seriousness as the OSCE How Long Does It Take? For UK-trained nurses, expect around three years for the degree, plus time to settle into your first role. For international nurses, timelines vary depending on how quickly you complete IELTS/OET, the CBT, and the OSCE many candidates register within six to twelve months of starting the process, especially with focused exam preparation. Paediatric Nurse Salary UK Newly qualified paediatric nurses typically start on NHS Band 5, with experienced nurses progressing to Band 6 or 7 as they take on specialist or leadership responsibilities. Salaries increase further in senior roles such as advanced nurse practitioner or ward manager, and additional allowances often apply in London and high-cost areas. Career Progression Opportunities Paediatric nursing offers clear routes for progression. Nurses can specialise in neonatal care, PICU, oncology, or community health visiting. Others move into education, research, or management, becoming ward managers, clinical nurse specialists, or nurse consultants. Continuous professional development, often supported by NHS trusts, keeps doors open throughout your